Abstract
Claim counts of operations in the 10th NDB Open Data (fiscal 2023, inpatient) were divided by the population on 1 October 2023, and the rates of open reduction of fracture (femur, forearm, lower leg) and two hip operations (hemiarthroplasty and total joint replacement) were lined up by sex and 5-year age group. It claims no new mathematical theorem and no new law.
First, the tables are consistent. In rows without "‐" (under 10) cells, the total equals the sum of the 38 sex-and-age groups, and in the population the sums over 5-year groups and sexes match the totals within the rounding width (Section 3).
Second, this is the core of the paper. The rate of open reduction of fracture (femur) rises at every step from 50–54 to 90+ for both sexes and peaks at 90+ (1966.2 for women, 833.9 for men). In the three steps from 75–79 on, it doubles every 4.25–5.84 years for both sexes (Sections 4 and 5).
Third, even for the same open reduction of fracture, the age peak differs by site. Women's forearm peaks at 80–84 (238.4) and falls in the two steps beyond. Women's lower leg peaks at 75–79 (67.4). Men's forearm peaks at 10–14 (85.7) and lower leg at 15–19 (63.6), with peaks at young ages (Section 4).
Fourth, even among hip operations, hemiarthroplasty (hip) peaks at 90+ for both sexes (790.1 for women), while total joint replacement (hip) peaks at 65–69 for both sexes (320.1 for women) and falls to 36.9 at 90+ (Section 4).
Fifth, the women-to-men ratio of rates differs by operation. The forearm is largest at 6.36 at 75–79, total joint replacement (hip) 4.47 at 55–59, and the femur peaks at 2.51 at 85–89 (Section 6).
Sixth, what separates them is which site, and which operation, is counted. "Fracture operations increase with age" holds up to 90+ for the femur but not for the forearm or lower leg.
Scope note: This paper claims no new mathematical theorem and no new law — claim counts and population are in public tables, and this paper only turned them into rates and lined them up. This paper is a structural interpretation of the shape of numbers in public aggregate data; it is not medical advice, not a diagnosis, and not a treatment recommendation. The author is not a physician. Decisions about individual health should be discussed with a physician or a medical institution. This is a preprint that has not been peer reviewed. It does not go into which operation is better, how operations are chosen, or how to prevent fractures. The numbers are claim counts under the medical fee schedule, not counts of people (the same person may be counted more than once). The operations are taken by their names, and which disease or injury they were done for cannot be seen in this table. Cells under 10 appear as "‐" in the table, and no rate is computed for them. Hospitals and prefectures are not compared. It is not an outlook for any one person. About the data: the 10th NDB Open Data (Ministry of Health, Labour and Welfare) is used under the Public Data License (Version 1.0), and the Population Estimates (e-Stat) under the Government Standard Terms of Use (Version 2.0); the rates and ratios in this paper were created by processing them. What this paper adds: lining up the rates of fracture operations by site and age, and showing that only the femur keeps doubling up to 90+ while the forearm and lower leg pass their peaks along the way, and that the peaks of the two hip operations are far apart, at 65–69 and 90+.
1. Notation and question
- Five operations: open reduction of fracture (femur), open reduction of fracture (forearm), open reduction of fracture (lower leg), hemiarthroplasty (hip), and total joint replacement (hip) (taken by their names in the fee schedule).
- Rate: inpatient claim counts in fiscal 2023 (April 2023 to March 2024) ÷ total population on 1 October 2023 × 100,000.
- Peak age: the 5-year group with the highest rate.
- Years to double: from the ratio r of rates between adjacent 5-year groups, 5 × log 2 ÷ log r (steps where the rate does not rise are "does not double").
Question: How does the rate of fracture operations rise with age? Is the age shape the same across sites and types of operation?
Observation 1.1: M002 measured how fast the adult death rate doubles with age. M059 showed that the share of fracture or fall among the main causes for needing care rises with age. This paper applies the same measure to the rates of fracture operations.
2. Survey and design
To be honest: the design was decided after seeing the tables.
| Content | |
|---|---|
| Tables | 10th NDB Open Data, medical procedures (claim counts), K operations, counts by section, sex, and age (fiscal 2023, "inpatient" sheet), and Population Estimates Table 3 (1 October 2023) |
| Noticed in the survey | Within each section there is a row per procedure, and "open reduction of fracture" is split by site (femur, forearm, lower leg, and so on). For the hip there are rows for hemiarthroplasty and total joint replacement |
| Ages | For each sex, 19 groups from 0–4 to 90+. The population at 90+ is the sum of 90–94, 95–99, and 100+ |
| Measures | Rate, peak age, years to double, women ÷ men |
3. Data and checks
Calculation 3.1 The 3 retrieved files were fixed by SHA-256, and the following was checked.
- On the NDB Open Data page, the link for "counts by section, sex, and age [729KB]" under "K operations" points to the retrieved file (001493186.xlsx). The sheets are outpatient, outpatient (add-ons), inpatient, and inpatient (add-ons).
- The heading of the inpatient sheet is "Claim months: April 2023 to March 2024, K operations, inpatient," with the note that values under 10 are shown as "‐." The age headings are 19 groups for each sex.
- The rows for the five procedures are present, and in the two rows without "‐" (femur and forearm) the total equals the sum of the 38 groups.
- The population is the 2023 column (thousands) of "Population and share by age (5-year groups) and sex (as of 1 October each year)." The difference between the sum of 5-year groups and the total, and between men + women and both sexes, are both at most 1 thousand.
Calculation 3.2 Totals of the five operations (fiscal 2023, inpatient)
| Procedure | Total (claims) | "‐" cells |
|---|---|---|
| Open reduction of fracture (femur) | 134,557 | 0 |
| Open reduction of fracture (forearm) | 64,429 | 0 |
| Open reduction of fracture (lower leg) | 46,123 | 2 |
| Hemiarthroplasty (hip) | 85,630 | 12 |
| Total joint replacement (hip) | 89,850 | 2 |
4. Rates and peaks by age
Calculation 4.1 Women's rates (per 100,000, ages 50+)
| Age | Femur | Forearm | Lower leg | Hemiarthroplasty (hip) | Joint replacement (hip) |
|---|---|---|---|---|---|
| 50–54 | 14.2 | 29.8 | 44.5 | 3.7 | 81.4 |
| 55–59 | 27.9 | 66.1 | 49.1 | 9.7 | 173.6 |
| 60–64 | 40.9 | 100.5 | 61.6 | 20.9 | 269.2 |
| 65–69 | 66.8 | 137.5 | 64.8 | 49.6 | 320.1 |
| 70–74 | 117.0 | 163.5 | 66.3 | 119.5 | 311.6 |
| 75–79 | 214.1 | 207.0 | 67.4 | 218.0 | 287.1 |
| 80–84 | 479.4 | 238.4 | 65.0 | 409.9 | 217.7 |
| 85–89 | 1083.0 | 224.8 | 54.7 | 654.2 | 131.7 |
| 90+ | 1966.2 | 147.7 | 37.9 | 790.1 | 36.9 |
Calculation 4.2 Men's rates (per 100,000, ages 50+)
| Age | Femur | Forearm | Lower leg | Hemiarthroplasty (hip) | Joint replacement (hip) |
|---|---|---|---|---|---|
| 50–54 | 14.3 | 20.9 | 37.9 | 3.1 | 22.8 |
| 55–59 | 21.9 | 25.0 | 44.2 | 6.3 | 38.8 |
| 60–64 | 32.9 | 24.6 | 48.7 | 14.6 | 64.6 |
| 65–69 | 46.3 | 27.7 | 51.1 | 28.8 | 78.0 |
| 70–74 | 68.1 | 28.8 | 49.0 | 58.8 | 72.5 |
| 75–79 | 111.9 | 32.5 | 49.8 | 99.3 | 67.0 |
| 80–84 | 202.6 | 38.4 | 51.3 | 186.0 | 53.1 |
| 85–89 | 432.0 | 41.2 | 53.5 | 333.8 | 40.9 |
| 90+ | 833.9 | 40.1 | 41.6 | 549.6 | 20.7 |
Observation 4.3: Open reduction of fracture (femur) and hemiarthroplasty (hip) peak at 90+ for both sexes, with the femur reaching 1966.2 for women. Women's forearm peaks at 238.4 at 80–84 and lower leg at 67.4 at 75–79, falling beyond. Men's forearm peaks at 10–14 (85.7) and lower leg at 15–19 (63.6). Total joint replacement (hip) peaks at 65–69 for both sexes (320.1 for women, 78.0 for men) and falls to 36.9 for women at 90+.
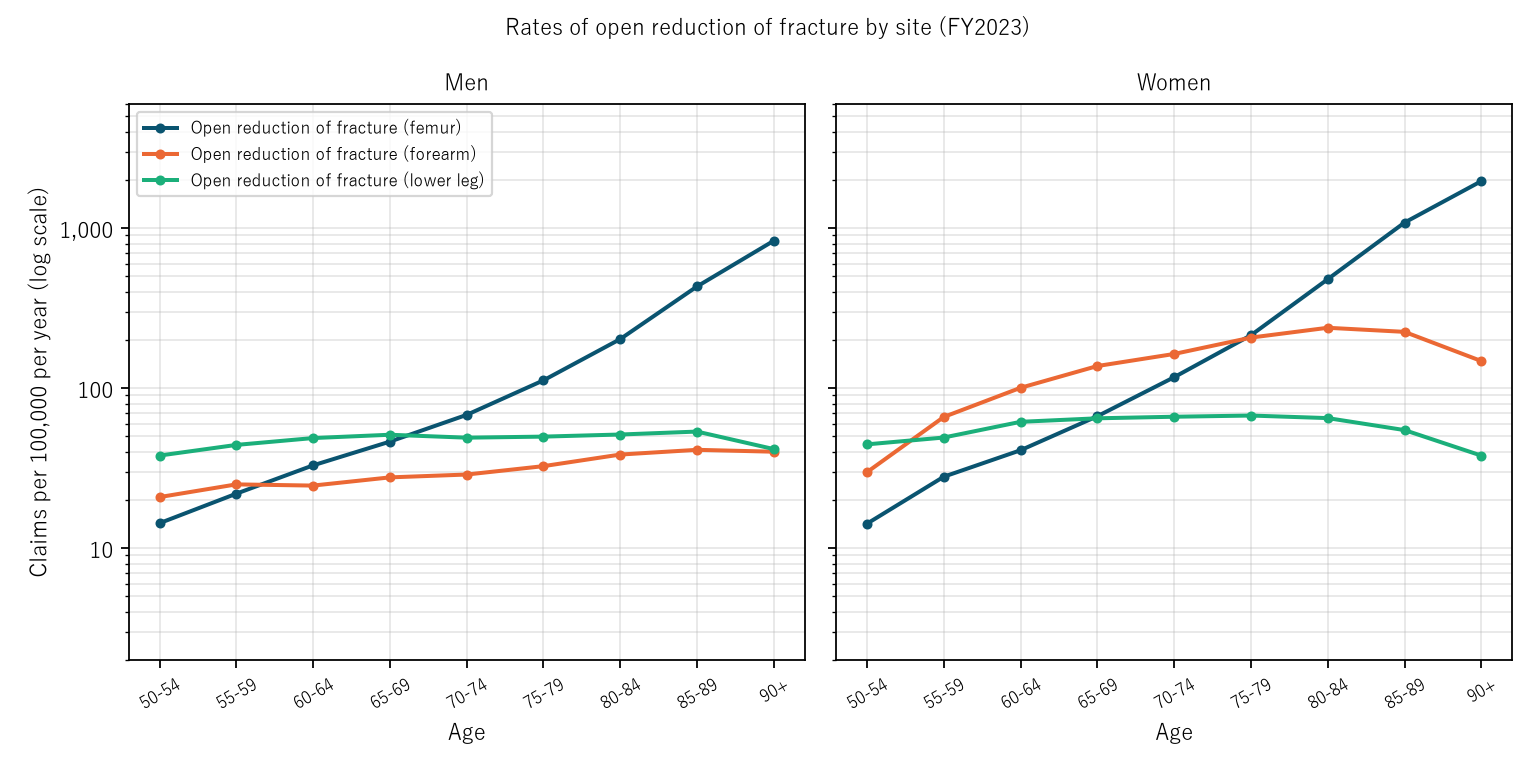
Figure 1: Rates of open reduction of fracture (per 100,000; vertical axis logarithmic; ages 50+). Men left, women right. Navy is femur, orange forearm, and green lower leg.
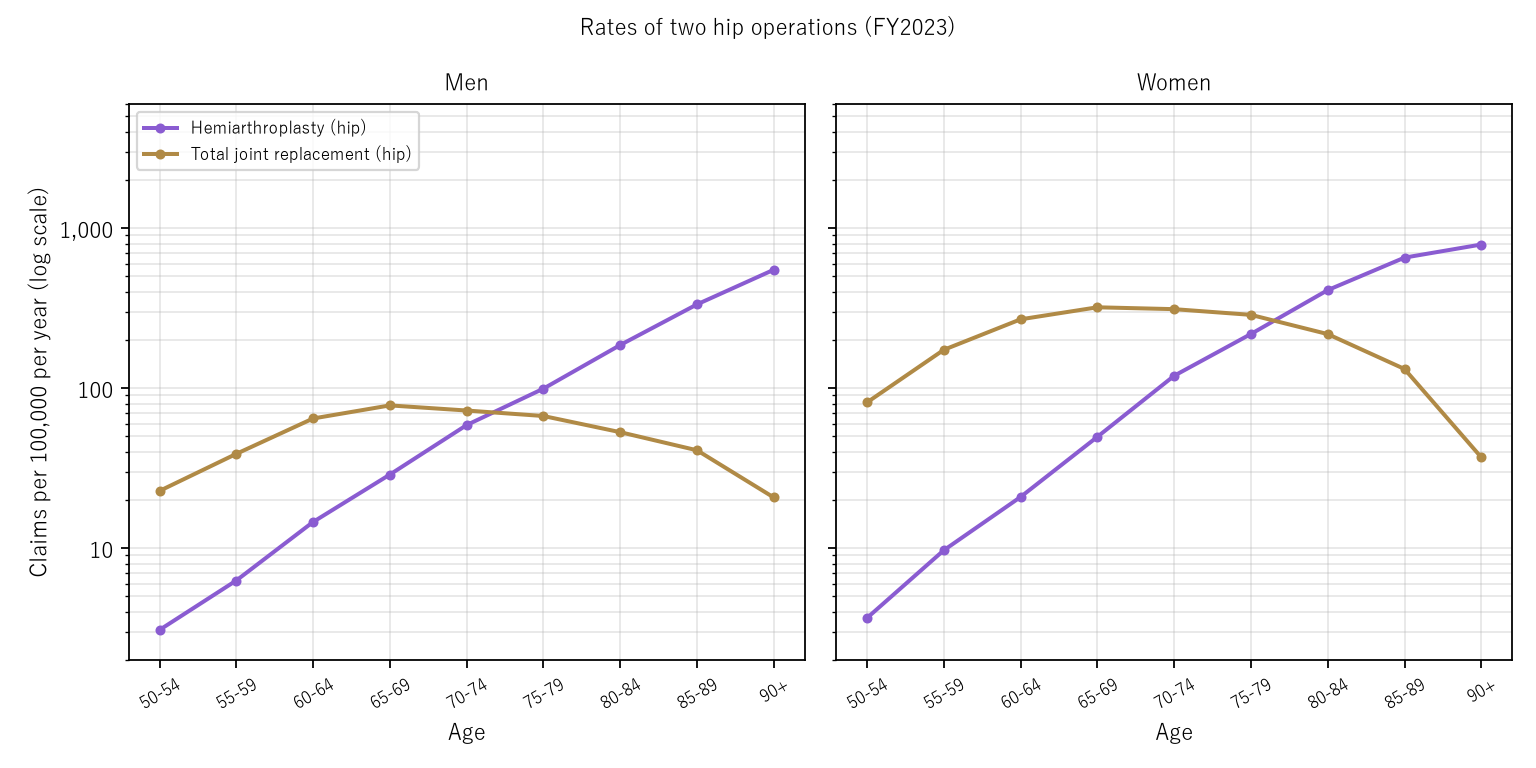
Figure 2: Rates of hemiarthroplasty (hip, purple) and total joint replacement (hip, gold) (per 100,000; vertical axis logarithmic). Men left, women right.
5. Core — only the femur keeps doubling up to 90+
Calculation 5.1 Years to double per 5-year step
| Step | Femur, men | Femur, women | Forearm, women | Lower leg, women | Joint replacement (hip), women |
|---|---|---|---|---|---|
| 50–54→55–59 | 8.16 | 5.13 | 4.36 | 35.19 | 4.58 |
| 55–59→60–64 | 8.50 | 9.09 | 8.26 | 15.33 | 7.90 |
| 60–64→65–69 | 10.14 | 7.08 | 11.06 | 68.43 | 20.01 |
| 65–69→70–74 | 9.00 | 6.17 | 19.96 | 154.49 | — |
| 70–74→75–79 | 6.98 | 5.74 | 14.71 | 202.02 | — |
| 75–79→80–84 | 5.84 | 4.30 | 24.52 | — | — |
| 80–84→85–89 | 4.58 | 4.25 | — | — | — |
| 85–89→90+ | 5.27 | 5.81 | — | — | — |
Observation 5.2: Open reduction of fracture (femur) rises at all 8 steps for both sexes, and doubles every 4.25–5.84 years in the three steps from 75–79 on. Women's forearm falls in the two steps beyond 80–84, and lower leg in the three steps beyond 75–79. Total joint replacement (hip) does not rise beyond 65–69 for both sexes. ("—" in the table marks steps where the rate does not rise.)
6. Women ÷ men
Calculation 6.1 Women-to-men ratio of rates (maximum at ages 50+)
| Procedure | Maximum women ÷ men | Age |
|---|---|---|
| Open reduction of fracture (femur) | 2.51 | 85–89 |
| Open reduction of fracture (forearm) | 6.36 | 75–79 |
| Open reduction of fracture (lower leg) | 1.35 | 75–79 |
| Hemiarthroplasty (hip) | 2.20 | 80–84 |
| Total joint replacement (hip) | 4.47 | 55–59 |
Observation 6.2: The women-to-men ratio is largest for the forearm, at 6.36 at 75–79. Total joint replacement (hip) is 4.47 at 55–59, femur 2.51 at 85–89, hemiarthroplasty (hip) 2.20 at 80–84, and lower leg 1.35 at 75–79. For the femur the ratio widens from 0.99 at 50–54 to 2.51 at 85–89.
7. Limitations
- The numbers are claim counts, not counts of people. The same person may be counted more than once, and the rate is not "the number of people per 100,000 who had an operation."
- Procedures are taken by name, and which disease or injury they were done for cannot be seen. These are not counts of fractures themselves.
- It is a comparison of age differences within one fiscal year (2023), not how the same people change. Cells under 10 are "‐" and no rate is computed for them.
- It does not go into which operation is better, how operations are chosen, or how to prevent fractures. Hospitals and prefectures are not compared. It is not an outlook for any one person.
Conclusion
The rate of open reduction of fracture kept rising up to 90+ for the femur, doubling every 4.25–5.84 years from 75–79 on. Women's forearm peaked at 80–84 and lower leg at 75–79, and men's forearm and lower leg peaked in the teens. Even among hip operations, hemiarthroplasty peaked at 90+ and total joint replacement at 65–69.
One thing separates them — which site, and which operation, is counted.
On hearing "fracture operations increase with age," check together which site and which operation the numbers are for, and at what age they pass their peak.
Data and reproduction
| Data | 10th NDB Open Data, medical procedures (claim counts), K operations, counts by section, sex, and age (Ministry of Health, Labour and Welfare website); Population Estimates Table 3 (Statistics Bureau, Ministry of Internal Affairs and Communications; e-Stat) (retrieved 26 September 2026) |
| Terms of use | NDB Open Data follows the Public Data License (Version 1.0), and e-Stat the Government Standard Terms of Use (Version 2.0). The rates and ratios in this paper were created by processing these and are not figures produced by the government |
| Scope | Japan, fiscal 2023 |
| Checker | 検算/M063.py (--zu also draws the figures). Every number in the text is taken from 検算/M063_output.txt |
| Raw data | The 3 retrieved files and SOURCES.md in data/ (URLs, retrieval date, SHA-256, terms of use, definitions and how calculations are set up) |
| Figures | 図/M063_zu1, 図/M063_zu2 (png, svg, English versions) |
References
- Ministry of Health, Labour and Welfare. 10th NDB Open Data, medical procedures (claim counts), K operations, counts by section, sex, and age (in Japanese) (accessed 26 September 2026). https://www.mhlw.go.jp/stf/seisakunitsuite/bunya/0000177221_00016.html
- Statistics Bureau, Ministry of Internal Affairs and Communications. Population Estimates, population as of 1 October each year, Table 3, population and share by age (5-year groups) and sex — total population (in Japanese). e-Stat (accessed 26 September 2026). https://www.e-stat.go.jp/
- Yamagishi, Y. (2026). The Speed at Which Adult Death Rates Double with Age Hardly Moved; What Fell Was the Level [M002]. Zenodo. https://doi.org/10.5281/zenodo.22963210
- Yamagishi, Y. (2026). The Leading Main Cause for Needing Care Is Dementia (16,743 per 100,000), but Choosing All That Apply It Is Frailty Due to Old Age (26,100) — By Age It Shifts from Cerebrovascular Disease (65–79) to Dementia (80–89) to Frailty (90+), and for Women the Top Three Are Within 98 [M059]. Zenodo. https://doi.org/10.5281/zenodo.22975921
Reference
Yamagishi, Y. (2026). Rates of Open Reduction of Fracture Peak at Different Ages by Site [M063]. Zenodo.
DOI: 10.5281/zenodo.22976616
YOI: https://www.yamagishiyuuki.com/yoi/M063
ORCID: 0009-0006-8587-3450
PDF (English) · PDF (Japanese) · Date proof of the English PDF (OpenTimestamps .ots) · SHA256SUMS
The record page for this paper (in Japanese, with the PDFs in each language and the date proof): YOI M063. This paper is a preprint and has not been peer reviewed.